

Women’s Health · Iron · Nutrition
Iron Deficiency in Women:
Why 1 in 3 Women Under 50 Are Affected
Fatigue. Trouble concentrating. Workouts that suddenly feel harder. Iron isn’t always the reason, but for millions of women, it’s a strong possibility worth understanding.
You can eat well, exercise regularly, sleep eight hours, and still find yourself wondering why your energy isn’t what it used to be.
Maybe your afternoon focus disappears earlier than it should. Maybe your usual workout suddenly feels disproportionately difficult. Maybe you’re tired despite sleeping normally.
There are dozens of possible explanations for symptoms like these.
But there is one common nutritional problem women may overlook: iron deficiency.
And it is far more prevalent than most people realize.
More than one in three younger women have iron deficiency
In 2024, researchers analyzed nationally representative data from more than 8,000 U.S. adults participating in the National Health and Nutrition Examination Survey.
Their finding was striking.
Among women older than 18 but younger than 50, 34% met the study’s criteria for absolute iron deficiency. Among men of the same age range, the figure was just 3%.[1]
34%
of U.S. women ages 18 to under 50 met criteria for absolute iron deficiency.
Men of the same age: 3% [1]
The symptom picture
Iron Deficiency
- Fatigue
- Difficulty focusing
- Lower cognitive performance
- Physical performance decrements
- Loss of hair
- Brittle nails
- Poorer skin complexion
That means iron deficiency wasn’t a niche problem confined to people with visibly poor diets or diagnosed anemia. It affected roughly one out of every three women under 50 in the study.
And importantly, iron deficiency and anemia are not the same thing.
Iron stores can decline before hemoglobin falls low enough to meet the definition of anemia.
Why women need so much more iron
Iron is essential because it sits at the center of one of the body’s most fundamental jobs: moving oxygen.
Most of the iron in your body is found in hemoglobin, the protein inside red blood cells that transports oxygen from your lungs to your tissues. Iron is also involved in myoglobin in muscle and numerous enzymes involved in cellular metabolism.
The body is good at conserving iron.
But there is one loss it cannot recycle: blood that leaves the body.
For women who menstruate, that happens repeatedly.
Studies of menstrual blood loss have demonstrated enormous variation from woman to woman, and this variation substantially affects dietary iron requirements.[2]
That biology is reflected in current U.S. dietary recommendations.
Recommended dietary allowance
Women 19–50 18 mg/day
Men 19–50 8 mg/day
More than twice the requirement.
Hallberg & Rossander-Hultén[2] plus NIH Office of Dietary Supplements dietary reference data.
Women therefore have a recommended iron intake more than twice as high during the years when menstruation is typical. After menopause, the recommended intake falls to 8 mg per day.
Iron deficiency can happen before anemia
This distinction matters.
Anemia describes an effect on the blood. Iron deficiency describes inadequate iron availability or stores. They overlap, but they are not interchangeable.
As iron availability declines, stored iron generally falls first. Only later can hemoglobin decrease enough to produce iron-deficiency anemia.
-
Stage 1
Iron stores decline
-
Stage 2
Iron-restricted erythropoiesis
-
Stage 3
Iron-deficiency anemia
That means someone can have low iron stores while still having a hemoglobin result that falls within the conventional normal range.
One major marker clinicians use is serum ferritin, which reflects stored iron. Ferritin has limitations (inflammation, for example, can raise it), so doctors may interpret it together with hemoglobin, transferrin saturation and other laboratory markers.
A large U.S. analysis published in The Lancet Haematology examined the relationship between ferritin and physiological signs of iron-restricted red-blood-cell production. In non-pregnant women, the researchers identified a ferritin threshold around 24–25 μg/L at which these changes became apparent.[3]
The practical takeaway isn’t to diagnose yourself from a number. It’s that:
A normal hemoglobin result doesn’t necessarily tell the entire iron story.
“Iron deficiency can precede iron-deficiency anemia.”
Ferritin, hemoglobin and other iron markers provide different pieces of the picture.
What can low iron feel like?
Symptoms alone can’t diagnose iron deficiency.
Fatigue, poor concentration and reduced exercise tolerance can result from stress, lack of sleep, thyroid disorders, infections, depression, inadequate calories and many other factors.
But controlled studies suggest that iron status itself can matter.
1. Fatigue
In a randomized controlled trial published in CMAJ, 198 non-anemic women with fatigue and low ferritin received either oral iron or placebo for 12 weeks. Fatigue scores declined in both groups, but declined significantly more in the iron-treated women.[4]
That doesn’t mean iron will improve fatigue in someone whose iron status is already adequate. It means that iron depletion itself can contribute to fatigue even before overt anemia is present.
2. Focus and cognitive performance
Iron is also relevant to the brain.
A blinded controlled study of women ages 18–35 compared cognitive performance across different iron-status groups. At baseline, iron-sufficient women performed better and completed certain cognitive tasks faster than women with iron-deficiency anemia. Improvement in iron status during treatment was associated with improvements in cognitive performance.[5]
Again, this doesn’t mean ordinary distraction or “brain fog” proves that someone has low iron. But cognition is another reason iron status matters beyond a standard blood count.

3. Exercise and physical performance
Iron also participates in muscle metabolism and energy production.
In a randomized, double-blind study of iron-depleted but non-anemic women, iron supplementation produced a greater improvement in endurance after aerobic training than placebo.[6]
Other research has similarly found impaired aerobic adaptation among women with low iron despite normal hemoglobin.
For active women, runners and endurance athletes in particular, iron status can therefore be relevant even when anemia isn’t present.
Fatigue
RCT evidence
Iron treatment reduced fatigue more than placebo in non-anemic menstruating women with low ferritin.[4]
View paper ↗Cognition
Controlled intervention
Iron status was associated with cognitive accuracy and processing performance in young women.[5]
View paper ↗Exercise
Randomized trial
Iron repletion improved adaptation to endurance training in iron-depleted non-anemic women.[6]
View paper ↗Who is particularly at risk?
Menstruation itself raises iron requirements, but the risk isn’t identical for every woman. Risk can be higher with:
- Heavy menstrual bleeding
- Pregnancy or the postpartum period
- Frequent blood donation
- Low overall dietary iron intake
- Vegetarian or vegan diets if iron intake and bioavailability aren't carefully managed
- Gastrointestinal disorders that interfere with absorption
- Some forms of chronic inflammation
Heavy periods deserve particular attention.
If you regularly soak through pads or tampons very quickly, need to double up protection, bleed for unusually long periods, pass large clots, or have bleeding that disrupts normal life, that warrants a conversation with a healthcare professional.
Simply adding more iron without understanding ongoing excessive blood loss can miss the underlying problem.
Don’t guess. Test.
If you repeatedly experience unexplained fatigue, reduced exercise tolerance or other concerning symptoms, particularly if you menstruate heavily, consider discussing iron testing with your healthcare professional.
A clinician may consider tests including:
Complete blood count (CBC)
Measures hemoglobin and red-blood-cell characteristics.
Ferritin
Provides information about stored iron.
Transferrin saturation
Provides information about how much circulating transferrin is carrying iron.
Additional tests can sometimes be useful depending on the clinical context.
Ferritin can also increase during inflammation, which is one reason interpretation isn’t always as simple as comparing one number with the laboratory’s reference range.
The goal should be to understand why iron is low, not simply to make a laboratory number go up.

But whether or not you’re deficient, your diet still has to replace the iron you lose.
Food is where daily iron intake begins
If testing reveals actual iron deficiency, treatment should be determined with your healthcare professional. Therapeutic iron doses can be very different from the amount of iron found in ordinary foods.
But nutrition still determines the iron your body encounters day after day.
Iron comes in two principal dietary forms:
- Heme iron, found in animal foods such as meat and seafood, is generally absorbed more readily.
- Non-heme iron, found in plant foods and fortified foods, is more sensitive to the other components of a meal.
Vitamin C is particularly interesting here.
In controlled feeding experiments, ascorbic acid substantially increased absorption of non-heme iron when consumed in the same meal.[7]
The amount of iron on the label therefore matters, but so does the context in which you consume it.
What does 18 mg actually look like?
½ cup lentils ≈3 mg
½ cup cooked spinach ≈3 mg
3 oz beef ≈2 mg
½ cup chickpeas ≈2 mg
NOVOS Bar 12.6 mg
Values for ordinary foods vary by preparation and serving size. NOVOS Bar amount is from the current Nutrition Facts panel.
For someone trying to reach 18 mg of iron every day, those numbers make one problem obvious: a typical snack contributes very little.
Protein bars usually compete on protein, calories or sugar.
Micronutrients are often an afterthought.
That’s the reason NOVOS Bar becomes particularly interesting for women who want to make everyday food more nutrient-dense.
The everyday option
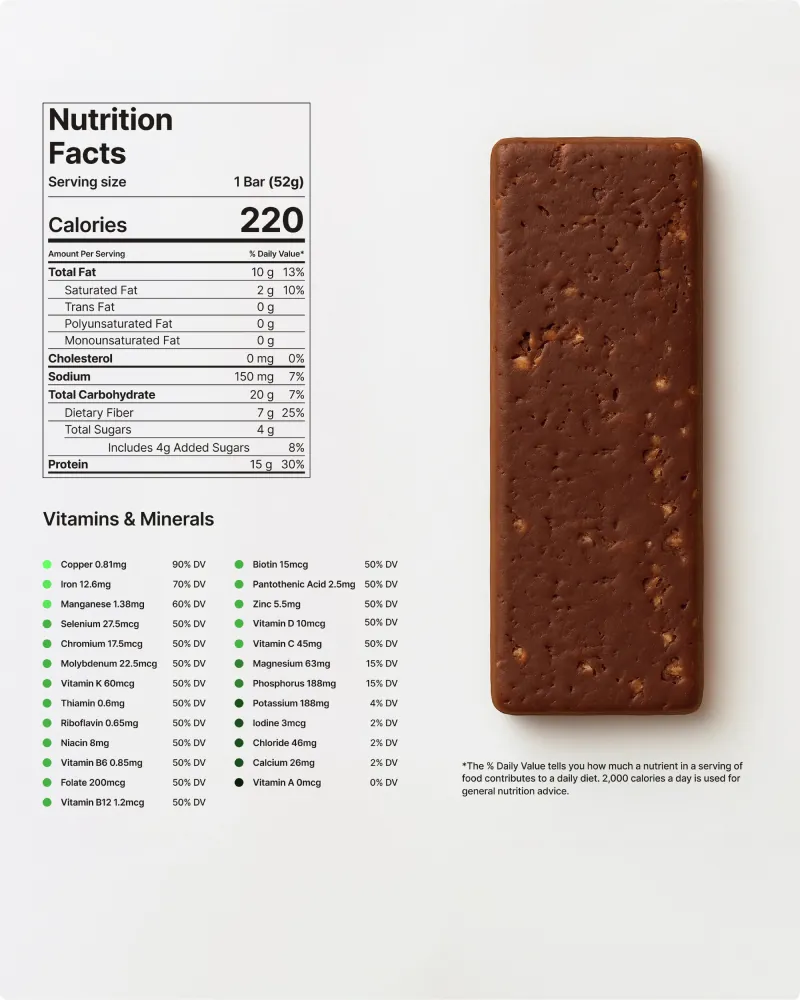
A snack that delivers 70% of the Daily Value for iron
One NOVOS Bar provides 12.6 mg of iron: 70% of the Daily Value in a single bar.
It also provides 45 mg of vitamin C (50% DV). That’s a useful pairing, because vitamin C can enhance the absorption of non-heme iron when consumed as part of the same meal.[7]
But NOVOS Bar wasn’t designed as an iron supplement. And iron is only one part of the formula. Each bar also provides:
- 15 g complete plant protein
- 6–7 g fiber
- 21 essential vitamins and minerals
- 1.5 g taurine
- 3 mg astaxanthin
- 200 mg Lion's Mane
- 200 mg Reishi
- 200 mg Cordyceps
That makes the proposition very different from simply taking an iron tablet. It’s a nutrient-dense food that happens to make a meaningful contribution to one of the nutrients menstruating women need most.

70%
of the Daily Value for iron
- + 50% DV Vitamin C
- + 15 g protein
- + 6–7 g fiber
Complete nutrition without making a snack feel like medicine
There’s another reason a food-first approach matters: you have to want to eat it consistently.
NOVOS Bar was developed around real-food ingredients including:
- organic olive oil
- organic sunflower and pumpkin seed butters
- honey
- rosemary
- cocoa
- fruits and vegetables
- functional mushrooms
And it is formulated without:
- refined seed oils
- sugar alcohols
- artificial sweeteners
- synthetic fats
- dyes
- gums
- preservatives
The product was developed with nationally acclaimed registered dietitian Brooke Alpert, M.S., R.D., C.D.N., alongside NOVOS scientists. Flavor and texture were developed with Van Nguyen, formerly pastry sous chef at Michelin Three-Star The French Laundry.
That combination matters. A theoretically perfect nutritional product does very little if it’s sitting untouched in the pantry.
Nutrition science meets pastry-chef craft.

Brooke Alpert, M.S., R.D., C.D.N.
Registered Dietitian · Best-Selling Author
Nutritional rigor

Van Nguyen
Former Pastry Sous Chef · The French Laundry
Flavor + texture
NOVOS Bar was designed to make unusually complete nutrition something you would actually choose as an everyday snack.
A bar isn’t a treatment for diagnosed iron deficiency
If laboratory testing shows that you’re iron deficient, especially if you have significant symptoms or heavy menstrual bleeding, don’t simply assume that eating more iron-rich foods is enough.
Your healthcare professional may recommend therapeutic oral iron, intravenous iron or additional investigation depending on the severity and cause.
NOVOS Bar is a food, not a treatment for iron deficiency or iron-deficiency anemia. Its advantage is simpler: it makes a highly iron-dense, nutritionally complete snack easy to fit into everyday life.
For someone who menstruates and is trying to meet an 18 mg daily iron requirement, 12.6 mg in a single food is meaningful.
And unlike a standalone iron nutrient, the same bar contributes protein, fiber, B vitamins, vitamins D and K, vitamin C and functional ingredients selected for whole-body nutrition.
Nutrition built for women
Your body loses iron.
Make your snack count.
One NOVOS Bar provides 12.6 mg of iron (70% DV), plus complete protein, fiber, essential vitamins and minerals, and five longevity nutrients.
One bar is a nutrient-dense snack · Subscribe or purchase once

This article is for educational purposes and is not intended to diagnose or treat iron deficiency, anemia, or any medical condition. Fatigue, difficulty concentrating, reduced exercise performance, and other symptoms discussed above have many potential causes. If you have symptoms that concern you, unusually heavy menstrual bleeding, or believe you may have an iron deficiency, speak with a qualified healthcare professional. NOVOS Bar is a food and is not intended to diagnose, treat, cure, or prevent disease.
References
-
[1]Tawfik YMK, Billingsley H, Bhatt AS, et al. Absolute and Functional Iron Deficiency in the US, 2017–2020. JAMA Network Open. 2024;7(9):e2433126.
DOI: 10.1001/jamanetworkopen.2024.33126Source for 34% of women older than 18 and younger than 50, 3% of men in the corresponding age group, and iron deficiency occurring without anemia.
-
[2]Hallberg L, Rossander-Hultén L. Iron requirements in menstruating women. American Journal of Clinical Nutrition. 1991;54(6):1047–1058.
DOI: 10.1093/ajcn/54.6.1047Menstrual iron loss and variability in women's iron requirements. Official U.S. RDA values (women 19–50: 18 mg; men 19–50: 8 mg; adults 51+: 8 mg) are from the NIH Office of Dietary Supplements.
-
[3]Mei Z, Addo OY, Jefferds ME, et al. Physiologically based serum ferritin thresholds for iron deficiency in children and non-pregnant women. The Lancet Haematology. 2021;8(8):e572–e582.
DOI: 10.1016/S2352-3026(21)00168-XPhysiological ferritin threshold around 24–25 μg/L in non-pregnant women. This is not presented as a universal diagnostic cutoff.
-
[4]Vaucher P, Druais PL, Waldvogel S, Favrat B. Effect of iron supplementation on fatigue in nonanemic menstruating women with low ferritin: a randomized controlled trial. CMAJ. 2012;184(11):1247–1254.
DOI: 10.1503/cmaj.110950A trial of therapeutic oral iron, not a trial of NOVOS Bar.
-
[5]Murray-Kolb LE, Beard JL. Iron treatment normalizes cognitive functioning in young women. American Journal of Clinical Nutrition. 2007;85(3):778–787.
DOI: 10.1093/ajcn/85.3.778Research on iron treatment, not on NOVOS Bar.
-
[6]Hinton PS, Giordano C, Brownlie T, Haas JD. Iron supplementation improves endurance after training in iron-depleted, nonanemic women. Journal of Applied Physiology. 2000;88(3):1103–1111.
DOI: 10.1152/jappl.2000.88.3.1103Physical performance and exercise adaptation with iron depletion in the absence of anemia.
-
[7]Hallberg L, Brune M, Rossander L. Effect of ascorbic acid on iron absorption from different types of meals. Human Nutrition: Applied Nutrition. 1986;40(2):97–113.
PMID: 3700141Vitamin C can enhance non-heme iron absorption when consumed as part of the same meal. The finished NOVOS Bar formulation has not undergone an iron-absorption study.